
Advanced ultrasound techniques now focus on the superior belly of the infraspinatus muscle as a primary indicator for hidden tendon pathology in the rotator cuff. This shift represents a significant departure from traditional diagnostic methods that primarily target the humeral insertion site, where dense anatomical overlap often obscures the full extent of soft tissue damage. In many clinical settings, full-thickness tears involving both the supraspinatus and infraspinatus tendons are frequently misidentified as isolated supraspinatus injuries, leading to surgical interventions that fail to address the complete scope of the pathology. By prioritizing the detection of secondary muscular changes, specifically selective atrophy within the superior compartment of the infraspinatus, medical professionals can now pinpoint complex lesions that were previously considered invisible during standard bedside examinations. This specialized diagnostic protocol provides a much-needed solution to a persistent blind spot in musculoskeletal medicine, ensuring that the localization of rotator cuff tears is both precise and comprehensive for every patient.
The intricate architecture of the shoulder’s posterior cuff necessitates such a nuanced approach, as the infraspinatus is not a monolithic structure but rather a multipennate muscle composed of three distinct functional bellies. These segments—the superior, intermediate, and inferior bellies—each possess unique fiber trajectories that eventually converge into a common tendon. The superior fibers follow a notably horizontal path and do not merely insert onto the middle facet of the greater tuberosity; they also interdigitate extensively with the supraspinatus tendon on the superior facet. This overlapping region, often referred to by anatomists as the transition septum or the posterior portion of the rotator cable, creates a complex biomechanical junction where injuries to one tendon frequently involve the adjacent tissue. Because the anterior fibers of the infraspinatus tendon are selectively continuous with the superior muscle belly, a tear at this specific junction triggers a rapid and highly localized physiological response that can be observed through high-resolution imaging.
Anatomical Foundations: Exploring the Posterior Cuff Structure
When a tear occurs at the transition septum, it initiates a process of neurogenic and disuse-related hypotrophy that is restricted solely to the superior compartment of the infraspinatus muscle. Traditional imaging techniques often fail to catch this early-stage deterioration because practitioners typically view the muscle as a single unit, missing the subtle volume loss in one specific belly while the remainder of the muscle appears perfectly healthy. This compartmentalized atrophy serves as a reliable biological marker, indicating that the structural integrity of the associated tendon fibers has been compromised. The physiological reality is that the muscle fibers begin to thin and change in texture almost immediately following a significant tear, providing a diagnostic window that precedes more obvious structural failures. Understanding this relationship between the specific muscle belly and its corresponding tendon section allows clinicians to interpret ultrasound findings with a level of detail that was previously reserved for more invasive or expensive imaging modalities.
The significance of identifying this selective thinning cannot be overstated in the context of modern orthopedic diagnostics. As the superior belly of the infraspinatus undergoes hypotrophy, it essentially signals the presence of a hidden anterior infraspinatus tear that might not be clearly visible at the footprint of the greater tuberosity. This diagnostic focus on muscle trophism—the state of nourishment and bulk within the tissue—allows for a screening-led approach that identifies pathology by looking at the “motor” of the shoulder rather than just the “cable.” By examining the infraspinatus fossa in a sagittal plane, sonographers can detect early signs of fatty infiltration and fibrous replacement long before the patient experiences a total loss of function. This proactive identification of muscular changes ensures that the diagnostic process remains ahead of the degenerative curve, facilitating earlier intervention and more accurate classification of the severity of the rotator cuff injury.
Diagnostic Methodology: Implementing the Muscle-First Approach
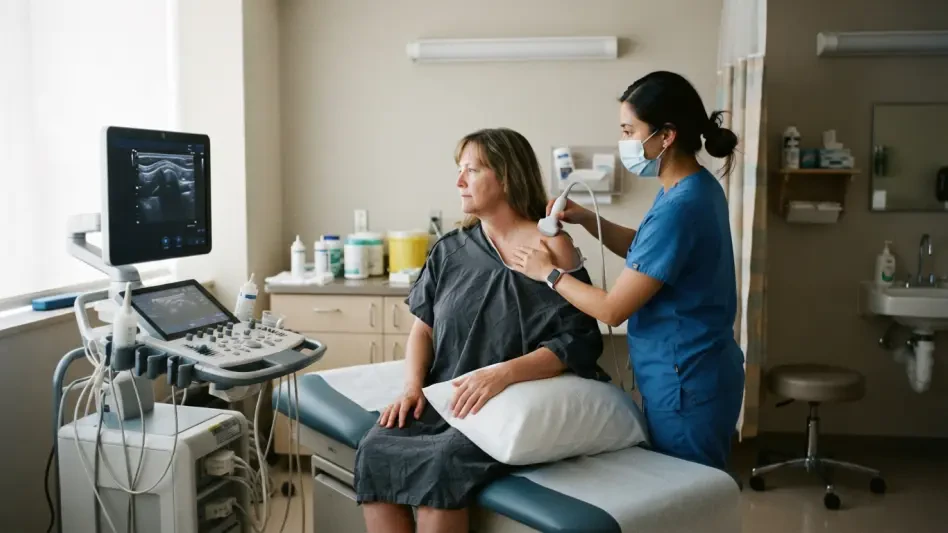
The core of the newly established diagnostic workflow involves a systematic B-Mode structural assessment to evaluate the superficial contour of the infraspinatus muscle. In a healthy shoulder, the epimysium-fascia contour typically presents as a flat or slightly convex surface, representing robust muscle volume and healthy tissue tension. However, when a hidden anterior infraspinatus tear is present, the superior belly exhibits a distinctive flattening or concavity that is easily recognizable to a trained sonographer. This change in shape is accompanied by increased echogenicity, appearing as a brighter or whiter area on the ultrasound screen, which indicates that healthy muscle fibers are being replaced by less elastic fatty or fibrous tissue. By starting the examination with this muscular overview rather than jumping straight to the tendon insertion, clinicians can quickly identify which patients require a more intensive investigation of the posterior rotator cuff territory.
Once the initial screening suggests muscle involvement, the protocol transitions to landmark-based axial scanning to precisely map the extent of the tear at the humeral footprint. This stage of the examination utilizes specific bony landmarks, such as the small, blunted osseous ridge on the greater tuberosity that naturally separates the superior and intermediate facets. By using this ridge alongside the Van Holsbeeck septum as anatomical anchors, the sonographer can accurately determine whether a tear has migrated across the border from the supraspinatus into the infraspinatus territory. This level of precision is further enhanced by the use of strain elastography, a technique that measures how much the muscle tissue deforms under controlled pressure to quantify its relative stiffness. By calculating a strain ratio that compares the affected superior belly to the healthy middle belly, researchers can objectively demonstrate a loss of tissue elasticity even in cases where structural atrophy is not yet visible to the naked eye.
Clinical Validation: Measuring the Impact of New Techniques
Recent clinical applications of this protocol in patients suffering from acute traumatic shoulder pain have demonstrated its remarkable accuracy and reliability. In multiple documented cases, an initial suspicion of an isolated supraspinatus tear was overturned by the new ultrasound workflow, which successfully identified combined tendon involvement that standard scans had missed. The quantitative data derived from these examinations remained consistently high, utilizing a standardized 0-to-2 grading scale to evaluate muscle flattening, echogenicity, and cross-sectional area reduction. The findings revealed that the superior bellies of the affected muscles showed significant pathology across all metrics, with mean scores indicating severe volume reduction and early-stage fatty infiltration. Furthermore, the interobserver agreement for these findings was found to be perfect, suggesting that the protocol is highly reproducible across different clinical environments and is not overly dependent on the subjective interpretation of an individual operator.
A critical component of this diagnostic success lies in the application of the Rotator Cable Theory, which explains the biomechanical shielding present in the shoulder. The rotator cable is a thick fibrous band that acts much like a suspension bridge, protecting the thinner crescent area of the supraspinatus from excessive stress and force. Because of this load-sharing mechanism, the supraspinatus muscle may not exhibit severe atrophy immediately following a tear, as the cable continues to transmit some level of force. In contrast, the anterior portion of the infraspinatus does not benefit from this same level of biomechanical protection, making it far more susceptible to rapid deterioration. Consequently, the superior infraspinatus belly acts as a reliable indicator—a “canary in the coal mine”—that atrophies earlier and more consistently than other parts of the rotator cuff. This early signal provides clinicians with the vital information needed to diagnose complex injuries before they progress to a state of irreversible muscle damage.
Comparative Advantages: Ultrasound Versus Magnetic Resonance Imaging
While Magnetic Resonance Imaging has long been considered the premier standard for evaluating rotator cuff integrity, high-resolution ultrasound now offers unique advantages that are particularly relevant in the 2026 clinical landscape. Comparative studies have shown that ultrasound protocols focusing on compartmental muscle atrophy can identify findings identical to those found on MRI, while providing the added benefit of being a bedside tool. The accessibility of ultrasound allows for immediate diagnostic confirmation during the initial consultation, reducing the time between injury and the commencement of a targeted treatment plan. Moreover, ultrasound is a cost-effective alternative that does not subject patients to the confined environment or potential contraindications associated with MRI scans. This makes it an ideal first-line diagnostic tool for orthopedic surgeons who require high-fidelity data to inform their decision-making process without the delays of traditional imaging schedules.
Beyond its static imaging capabilities, ultrasound allows for dynamic functional assessments that static MRI simply cannot replicate. Clinicians can perform the Resisted External Rotation Test while simultaneously scanning the infraspinatus muscle, providing a real-time view of how the muscle bellies respond to physical stress. This functional assessment offers deep insights into the patient’s actual performance and the impact of the tear on shoulder stability. Although the current findings are supported by consistent clinical data, future research is expected to incorporate even more advanced technologies, such as shear-wave elastography. This will provide an absolute quantitative measurement of tissue stiffness, further refining the protocol and moving away from semi-quantitative grading. As these technologies continue to evolve from 2026 to 2028, the ability to detect hidden pathology will only become more precise, ultimately setting a new standard for musculoskeletal diagnostics worldwide.
Precision Orthopedics: Guiding Surgical Strategy and Recovery
The implementation of this specialized ultrasound protocol represented a fundamental shift in how shoulder pathologies were managed in clinical practice. By successfully identifying hidden infraspinatus involvement through the observation of selective superior belly atrophy, clinicians moved beyond the traditional “torn or not torn” binary toward a more sophisticated, anatomical understanding of each unique injury. This level of detail proved to be invaluable for surgeons, as the knowledge of a tear’s extension into the infraspinatus dictated significant changes in the surgical approach. It required the application of different suture tensioning techniques and specific anchor placements designed to restore the natural force couple of the shoulder joint. This precision ensured that the mechanical balance of the rotator cuff was fully reinstated, which was essential for long-term joint health and the prevention of future degenerative changes.
For the patients involved, the adoption of this screening-led diagnostic philosophy resulted in significantly improved functional outcomes and a reduced risk of post-surgical recurrence. The ability to visualize the true state of the tendon by examining the health of the muscle motor paved the way for highly individualized orthopedic care that addressed the root cause of the patient’s dysfunction. Medical facilities that integrated this protocol found that they could provide more accurate prognoses and more effective rehabilitation schedules, as the treatment was based on the actual physiological state of the entire rotator cuff complex. The transition to this muscle-first approach ultimately advocated for a more holistic view of shoulder health, ensuring that no part of a complex tear remained hidden from the clinician’s view. These advancements solidified ultrasound’s role as an indispensable tool in modern orthopedics, transforming the standard of care for millions of patients.